
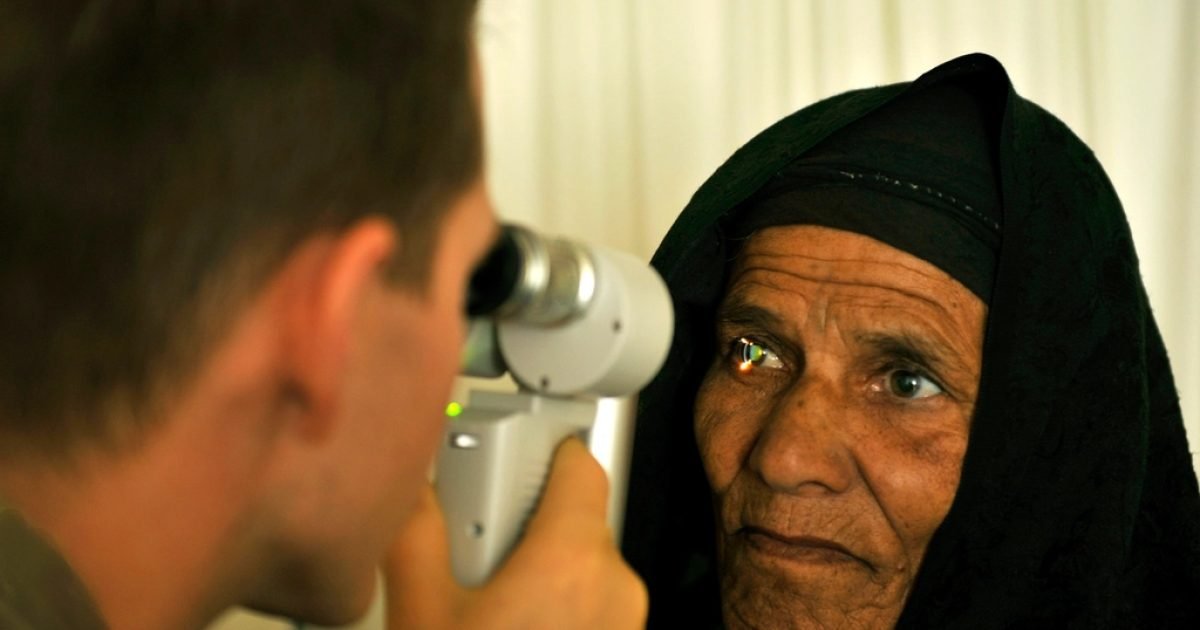
Two Questions, One Urgent
Floaters generate two entirely different questions, and mixing them up is the risk in this topic. The first is cosmetic and chronic: those drifting specks are annoying, will they go away, can anything remove them? The second is urgent and time-limited: is this particular change a sign that the retina is tearing?
The second question deserves priority, because the answer has a deadline. Most floaters are harmless. A sudden change in them can be the earliest sign of a retinal tear, where treatment within days rather than weeks affects whether vision is preserved. Anyone reading this because something changed today should read the warning signs section first and then call an eye specialist rather than finishing the article.
What Floaters Actually Are
The eye is filled with vitreous, a clear gel that is roughly 99% water held in a scaffold of collagen fibers. In youth this gel is uniform and firmly attached to the retina at the back of the eye.
With age it changes. The gel liquefies progressively, a process called syneresis, and the collagen scaffold clumps into strands and aggregates. Those clumps float in the liquefied gel and cast shadows on the retina. What you see is not the clump itself but its shadow, which is why floaters are more visible against a bright uniform background such as a white wall or a clear sky, and why they drift when your eye stops moving. They are moving with the gel, not with your gaze.
This process is close to universal. It starts earlier in people who are nearsighted, and it accelerates after cataract surgery or eye trauma.
Posterior Vitreous Detachment
The process has a milestone. As the vitreous liquefies and shrinks, it eventually separates from the retinal surface. This is posterior vitreous detachment, and it happens to most people, typically between the ages of 50 and 70.
It is normal, and it is the single most important event in this topic, because of how it can go. Usually the gel peels away cleanly and the result is a new large floater, often a ring or a cobweb, sometimes with brief flashes as the gel tugs on the retina during separation. Occasionally, and unpredictably, the vitreous is more firmly attached at some point, and instead of separating cleanly it pulls hard enough to tear the retina. A tear allows fluid underneath, and that can progress to retinal detachment.
A meaningful minority of people who present with symptomatic posterior vitreous detachment turn out to have a retinal tear, which is why the standard recommendation for a sudden change in floaters is a dilated examination rather than reassurance over the phone. Cleveland Clinic's overview of eye floaters covers the presentation and the reason for urgency.
The Warning Signs
| What you notice | What it may mean | What to do |
|---|---|---|
| A few floaters, unchanged for years | Ordinary age-related vitreous change | Mention at your next routine eye exam |
| One new large floater | Possible posterior vitreous detachment | Prompt evaluation, ideally within days |
| Sudden shower of many new floaters | Possible retinal tear or vitreous hemorrhage | Same-day evaluation |
| Flashes of light, especially in the periphery | Vitreous traction on the retina | Same-day evaluation |
| A curtain or shadow across vision | Possible retinal detachment in progress | Emergency, immediately |
| Loss of peripheral vision | Possible retinal detachment | Emergency, immediately |
The distinction that matters is change. A stable population of floaters that has been present for a decade is a different clinical situation from a sudden increase this morning, even if the specks look similar.
Why Floaters Become Less Noticeable
People frequently report that a floater that was intolerable six months ago no longer bothers them. Two things contribute.
The physical one: floaters can settle out of the direct visual axis over time, moving to a position where they cast fewer shadows on the central retina.
The neurological one: the brain adapts. Visual processing suppresses stable, uninformative signals, which is the same mechanism that stops you noticing your own nose. This is genuine relief and it is not removal. The floater is still there, and it will reappear against a bright sky or when you go looking for it.
This matters for evaluating any product or intervention: the natural course of a floater's bother is downward, which makes uncontrolled reports of improvement extremely difficult to interpret.
Not All Floaters Are the Same
The word floater covers several different things, and the differences matter for both prognosis and treatment.
Diffuse collagen strands are the ordinary kind: wisps, threads, and small specks from the gradual clumping of the vitreous scaffold. They accumulate slowly, and they are the ones the brain adapts to most successfully.
A Weiss ring is the large, often circular floater that appears when the vitreous separates from the optic nerve head during posterior vitreous detachment. It is usually a single distinct shape, and its arrival marks an event rather than a gradual change, which is why it warrants examination.
Blood is a different matter entirely. A vitreous hemorrhage produces a sudden shower of small dark specks, often described as soot, smoke, or a swarm of gnats. It means something is bleeding inside the eye, and the causes include a torn retinal vessel and proliferative diabetic retinopathy. This is the presentation that most reliably signals a problem requiring treatment.
Inflammatory cells from uveitis can also appear as floaters, usually alongside pain, redness, or light sensitivity.
The reason to distinguish them is that only the first category is reliably benign, and the descriptions people give often contain the information a clinician needs: a single ring versus a sudden swarm of dark dots point in different directions.
What Can Actually Be Done
Nothing, usually. For most people this is the recommendation, and it is not dismissiveness. It reflects a genuine risk calculation: the interventions carry real risk, and most floaters cause a nuisance rather than functional impairment.
Vitrectomy. Surgical removal of the vitreous does eliminate floaters. It also carries meaningful risks, including cataract formation in a large proportion of patients who have not had cataract surgery, and small but serious risks of retinal detachment and infection. It is reserved for cases where floaters substantially impair function, and the threshold is high for good reason.
YAG laser vitreolysis. A laser is used to break up larger floaters. The evidence is limited, one small randomized trial reported improvement in a subjective measure, results appear better for certain floater types, and it is not universally offered. It is a real option with a thin evidence base rather than a standard treatment.
Time. Adaptation is the most common resolution, and it is the one that costs nothing and carries no risk.
Where a Supplement Fits
Eye supplements are a large category, and it is important to separate two different questions, because the marketing does not.
For age-related macular degeneration, there is genuine trial evidence. The AREDS2 formulation reduced progression to advanced disease in people who already had intermediate macular degeneration. That is a specific formulation, tested in a large trial, for a specific condition and a specific population. It is one of the few real success stories in supplement research, and it says nothing about floaters.
For floaters, the evidence is close to absent. One small pilot trial of an enzyme blend reported a modest change in a subjective floater measure, which is preliminary at best and would need replication in a properly controlled trial to mean anything. The mechanism problem is more fundamental: floaters are a physical alteration in the structure of a gel, and no oral product has been shown to reverse it.
VisiFlora is one commercial example in the eye supplement category, sold with a 60-day refund window. We found no independent trials of the finished formula, so the available evidence is insufficient to say what it does. The important point for this article is narrower and clearer: nothing in this category addresses floaters, and no supplement substitutes for the dilated examination that a sudden change in floaters requires. Anyone with existing eye disease or on medication should discuss supplements with their ophthalmologist. Our full VisiFlora review examines the formula and its claims.
When to See a Doctor
Same-day evaluation for a sudden increase in floaters, new flashes, a shadow or curtain in the visual field, or loss of peripheral vision. These are the classic symptoms of retinal tear and detachment, and the outcome depends substantially on timing: a tear treated promptly is generally a straightforward procedure, while a detachment involving the macula carries a worse visual prognosis even after successful repair.
Routine evaluation for stable floaters is reasonable at your regular exam. People with high myopia, a history of eye trauma or surgery, or a family history of retinal detachment carry higher risk and should have a lower threshold for calling. The National Eye Institute's page on retinal detachment describes the symptoms and risk factors.
Frequently Asked Questions
What are eye floaters?
Floaters are shadows cast on the retina by clumps of collagen and cellular debris suspended in the vitreous, the gel that fills the eye. They appear to drift because they move with the vitreous rather than with your gaze. Most become more noticeable with age as the vitreous liquefies and its collagen structure clumps together.
When are floaters an emergency?
A sudden increase in floaters, new flashes of light, a curtain or shadow moving across the visual field, or a loss of peripheral vision requires same-day evaluation by an eye specialist. These can indicate a retinal tear or detachment, where treatment delay affects the outcome. A few longstanding, unchanged floaters are a different situation.
Do floaters ever go away?
The physical opacity usually remains, but many people notice it less over months as the brain adapts and the floater settles out of the central visual axis. That is neuroadaptation rather than disappearance. Floaters that are unchanged for years and cause no other symptoms are generally considered benign.
Can supplements dissolve floaters?
No supplement has been shown to eliminate floaters. One small pilot trial of an enzyme blend reported a modest reduction in a subjective floater measure, which is preliminary and far from establishing efficacy. The structural change producing floaters is a physical alteration of the vitreous gel, and available evidence is insufficient to suggest that any oral product reverses it.
Why do I see floaters more against a bright sky?
Floaters are visible as shadows, and shadows show up best against a bright, uniform background. A white wall, a blue sky, or a bright screen provides exactly that. The same floater is often invisible in a textured or dimly lit environment, which is why people notice them in some settings and not others.
The Bottom Line
Floaters are shadows from collagen clumps in a gel that liquefies with age, and for most people they are a harmless nuisance that the brain gradually learns to ignore. The part that matters is change: a sudden shower of new floaters, new flashes, or a shadow in the peripheral vision can be the first sign of a retinal tear, and that is a same-day call rather than a wait-and-see. Established floaters have limited treatment options, all with real risk, which is why watchful adaptation remains the usual recommendation. No supplement has been shown to remove them, and nothing in that category substitutes for a dilated exam when something changes.